
Cervical Myelopathy: Protecting Your Spinal Cord Before Damage Sets In
Clumsy hands, dropping things, feeling off-balance. These changes are easy to blame on getting older, but they can be signs that the spinal cord in your neck is being squeezed. Catching it early matters.
What Is Cervical Myelopathy?
Cervical myelopathy means the spinal cord in your neck is being compressed and is starting to malfunction. The spinal cord carries every signal between your brain and your body, so pressure on it can affect your hands, arms, legs, balance and even bladder control.
Unlike a pinched nerve, which usually causes pain down one arm, myelopathy often causes surprisingly little pain. Instead, it creeps in as numbness, clumsiness and unsteadiness that slowly worsen over months or years.
Myelopathy tends to progress, and spinal cord damage does not always fully recover once it has happened. That’s why the goal of treatment is to take pressure off the cord before more function is lost. Surgery to decompress the spinal cord is very effective at stopping progression, and many patients regain strength and coordination afterward.
What’s Happening in Your Neck
The spinal cord runs through a bony tunnel called the spinal canal. Over time, that tunnel can narrow from several directions at once:
- From the front: bulging or herniated discs and bone spurs
- From the back: thickened, buckled ligament (the ligamentum flavum)
- From the ligament along the spine: a condition called OPLL, where a ligament slowly turns to bone
- From birth: some people simply have a narrower canal, leaving less room for these changes
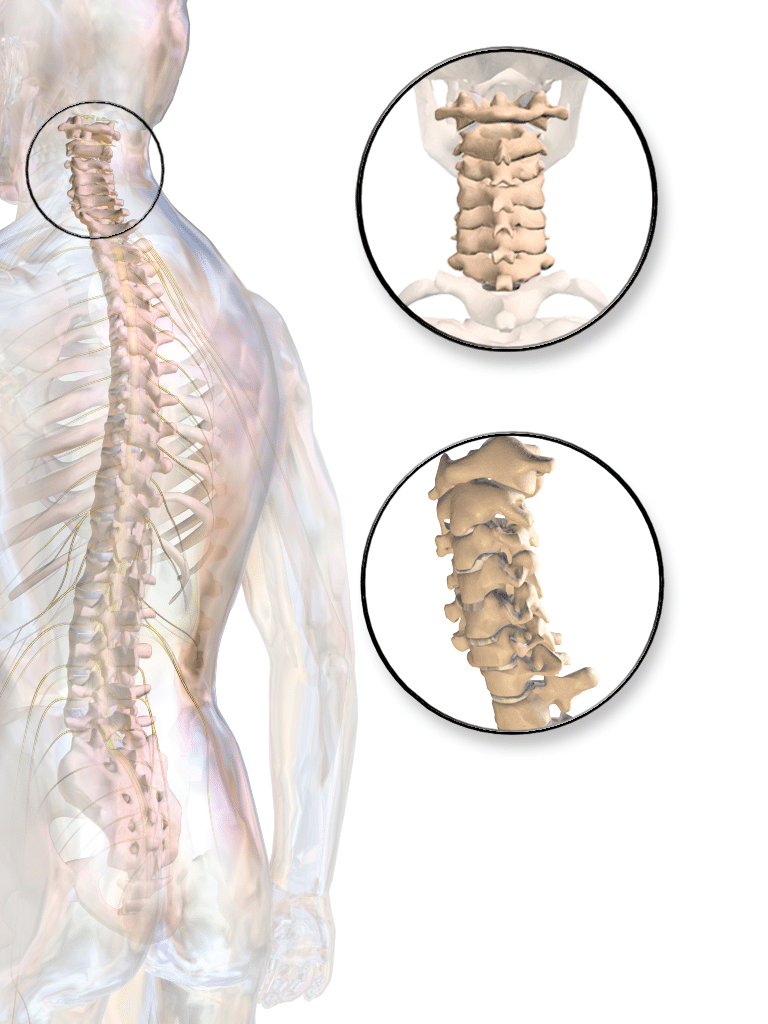
Symptoms of Cervical Myelopathy
Common symptoms
- Numbness or tingling in the hands, often both hands
- Clumsiness: trouble with buttons, zippers, handwriting or picking up coins
- Dropping things more often
- Problems with balance or feeling unsteady when walking
- Neck stiffness or pain
Symptoms patients often ignore
- Needing to hold the handrail or touch the wall when walking
- Typing or texting errors that weren’t there before
- An electric shock down the spine or arms when bending the neck forward
- Legs that feel stiff or heavy
- Bladder urgency or frequency in later stages
When to seek care right away: Rapidly worsening weakness, new trouble walking, falls, or loss of bladder or bowel control need urgent evaluation. Call 911 or go to the nearest emergency room if symptoms change suddenly, especially after a fall or neck injury.
Causes and Risk Factors
- Age-related wear (cervical spondylosis): the most common cause, usually after age 50
- Spinal stenosis and large disc herniations
- OPLL, which is more common in people of East Asian descent
- A congenitally narrow canal
- Less commonly, injury, rheumatoid arthritis, tumors or infection
How We Diagnose Cervical Myelopathy
- Neurological exam: hand strength and coordination, reflexes (including the Hoffmann sign, a reflex in the fingers that can signal cord compression), sensation, and how you walk and balance
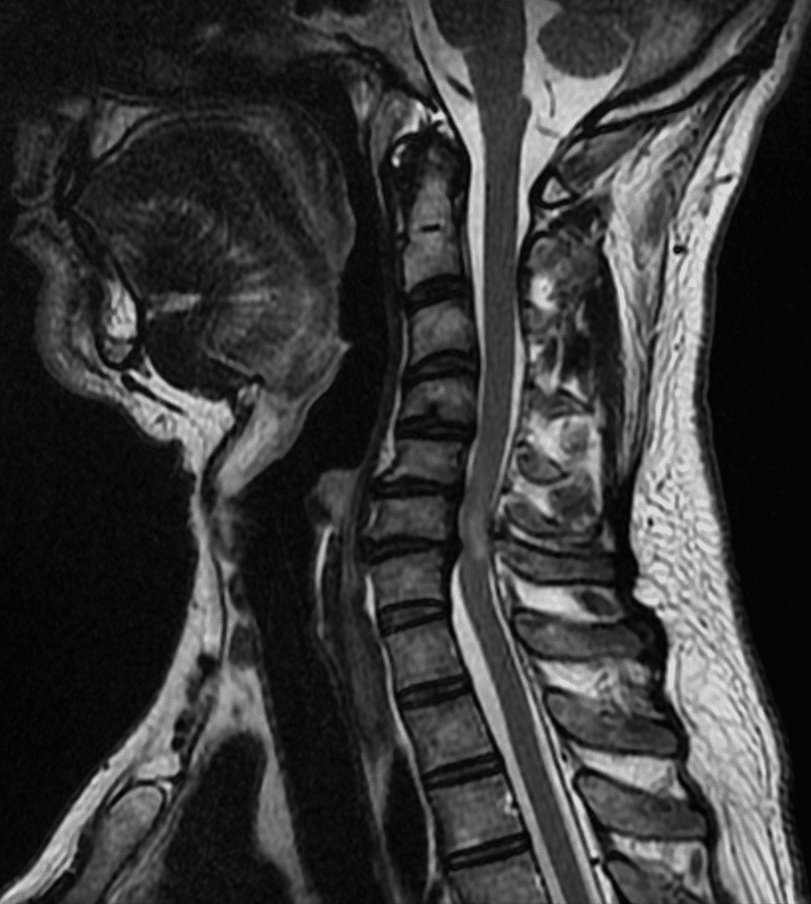
- MRI of the neck: shows where and how much the spinal cord is compressed and whether the cord itself shows signs of injury
- CT scan: shows bone spurs and OPLL in detail and helps plan surgery
- X-rays with bending views: check alignment and stability
- Nerve studies when needed: to rule out carpal tunnel syndrome or peripheral neuropathy, which can cause similar hand symptoms
Treatment Options
Non-surgical care
For mild myelopathy that is not progressing, careful monitoring may be reasonable. This means regular exams and imaging, physical therapy for balance and strength, and avoiding activities that put the neck at risk, such as neck manipulation or high-impact sports. Non-surgical care cannot relieve the pressure on the cord, so any sign of worsening is a reason to revisit surgery.
When surgery makes sense
Surgery is generally recommended for moderate or severe myelopathy, or for any myelopathy that is getting worse. The goal is to give the spinal cord room again, stop further damage and give it the best chance to recover. Depending on where the compression is, options include:
- Anterior cervical discectomy and fusion (ACDF): removes the discs and bone spurs pressing on the front of the cord
- Cervical artificial disc replacement: for selected patients with compression at one or two discs, decompresses the cord while preserving motion
- Cervical laminectomy with posterior cervical fusion: opens the canal from the back when compression involves several levels
Dr. Grunch will explain which approach fits your anatomy, and why.
Why Choose Dr. Betsy Grunch for Cervical Myelopathy
- Duke-trained: neurosurgical residency and spine research fellowship at Duke University School of Medicine, where she received the Spine Young Investigator Award
- Experience you can count on: in practice since 2013, performing 400 to 600 surgeries a year and more than 5,000 procedures over her career
- Front and back approaches: experience with both anterior and posterior neck surgery, plus motion-preserving disc replacement, so your operation is chosen for your spine
- Surgery only when it helps: board-certified (FAANS, FACS, FCNS), she starts with the least invasive treatment that will work
- Clear answers: known online as Ladyspinedoc, she makes sure you understand your imaging and every option in front of you
What to Expect If You Need Surgery
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your MRI and CT and choose the right approach. Our team coordinates pre-operative testing and reviews your medications.
Procedure day
Front-of-neck surgeries (ACDF or disc replacement) typically take one to three hours, and many patients go home the same day or after one night. Posterior laminectomy and fusion usually involves a hospital stay of a few days.
Recovery timeline
- Days 1-7: walking right away; a sore throat or mild trouble swallowing is common after front-of-neck surgery
- Weeks 1-6: gradual return to light activity; no heavy lifting; some patients wear a collar
- Weeks 6-12: physical therapy for strength, balance and hand coordination
- Months 3-12: continued recovery of hand function and walking; improvement can continue for a year or more
Frequently Asked Questions
Will my symptoms go away after surgery?
Surgery is most reliable at stopping myelopathy from getting worse. Many patients also see improvement in hand function, balance and walking, but nerve damage that has been present a long time may not fully reverse. That’s why earlier evaluation leads to better results.
Is this the same as a pinched nerve?
No. A pinched nerve (radiculopathy) affects one nerve root and usually causes pain down one arm. Myelopathy affects the spinal cord itself and can affect both hands, both legs and balance. Some people have both.
Can I just watch it?
For mild, stable myelopathy, careful monitoring can be appropriate. If you notice any worsening in your hands, walking or balance, it’s important to be re-evaluated promptly.
Should I avoid chiropractic neck adjustments?
Yes. With known spinal cord compression, forceful neck manipulation can be risky. Talk with your surgeon before any neck treatment.
How is myelopathy different from carpal tunnel?
Carpal tunnel causes numbness in part of the hand from a pinched nerve at the wrist. Myelopathy often affects both hands, causes clumsiness rather than just numbness, and may come with balance problems. An exam and nerve studies sort it out.
Take the First Step Toward Relief
Whether you need a diagnosis, a treatment plan or a second opinion, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
This page is for educational purposes only and is not a substitute for medical advice. If you have sudden weakness, trouble walking, or loss of bladder or bowel control, call 911 or go to the nearest emergency room.