
Stabilizing Broken Vertebrae and Protecting the Spinal Cord
If someone has a fall, car accident or other injury followed by severe neck or back pain, numbness, tingling, weakness, or trouble controlling the bladder or bowels, call 911. Don’t move them unless they are in danger. A spinal fracture can injure the spinal cord.
A broken bone in the spine, whether from a fall, a car accident or weakened bone, can be frightening and painful. When a fracture is unstable or putting pressure on the nerves, surgery can often correct the problem by stabilizing the spine, protecting the spinal cord and letting you get back on your feet.
What Is Spinal Fracture Surgery?
Spinal fracture surgery stabilizes broken vertebrae so they can heal in good alignment and stop pressing on the spinal cord or nerves. Most spinal fractures heal without surgery, but some leave the spine unstable or crowd the spinal canal. This page covers the main ways those fractures are treated:
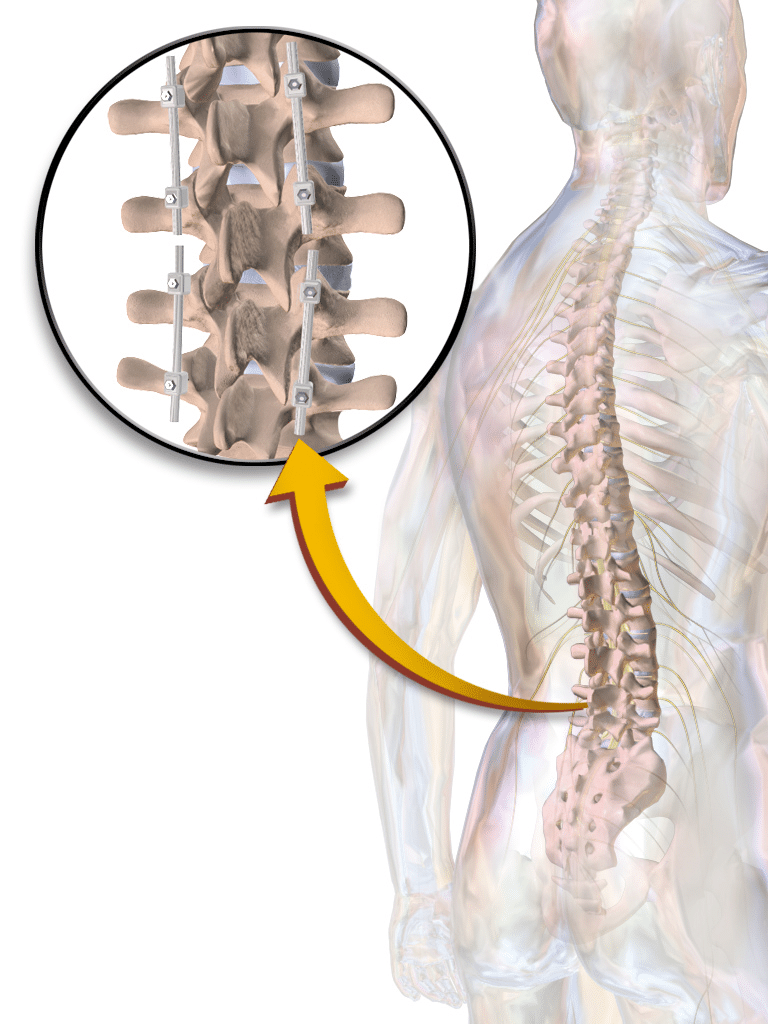
- Vertebral fracture stabilization: screws and rods hold the broken vertebrae steady while they heal, often placed through small incisions.
- Burst fracture repair: in a burst fracture, the vertebra breaks into several pieces, and fragments can push back into the spinal canal. Surgery removes the pressure and rebuilds the spine’s support.
- Stabilization after trauma: high-energy injuries can tear the ligaments and joints that hold the spine together. Surgery realigns and fuses the injured segment to protect the spinal cord.
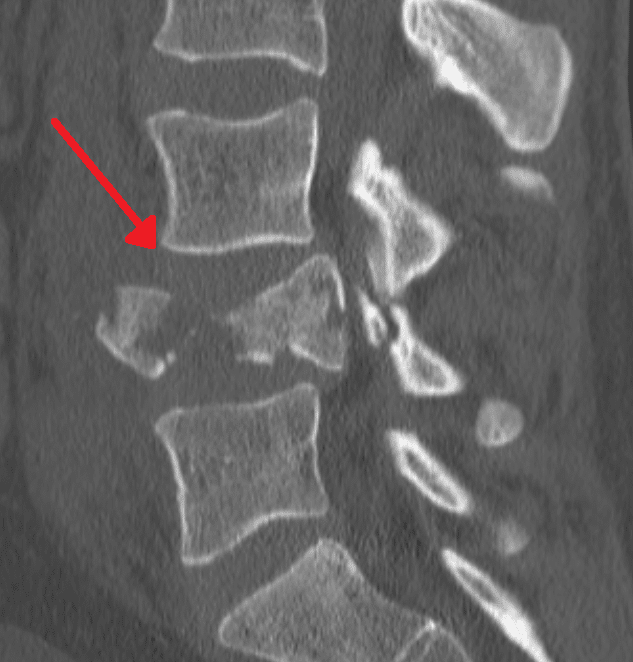
Simple compression fractures from osteoporosis are often treated with kyphoplasty or vertebroplasty instead. When the front of a vertebra is badly crushed, a corpectomy may be needed to rebuild it.
Who Needs Spinal Fracture Surgery?
- An unstable fracture, where the bones or ligaments can no longer hold the spine in alignment
- A burst fracture with significant collapse or bone fragments in the spinal canal
- Weakness, numbness or other signs of spinal cord or nerve injury
- Fracture-dislocations and seat-belt (flexion-distraction) injuries
- A fracture that is causing the spine to collapse or round forward over time
- A fracture through bone weakened by a tumor or infection (metastatic spine disease)
- Pain that keeps you from getting up and moving despite bracing
Many stable fractures heal well with a brace, pain control and a gradual return to activity. Your surgeon reviews your X-rays, CT and MRI to decide whether your fracture is stable and whether surgery will help.
Treatment Without Surgery
- Bracing: a custom or off-the-shelf brace to support the spine while it heals
- Pain control: medications to keep you comfortable enough to walk
- Early walking: getting up and moving, with repeat X-rays to make sure the fracture isn’t shifting
- Physical therapy: once the fracture has started to heal
- Bone health treatment: testing and treatment for osteoporosis when the bone is weak
When a fracture is unstable, is pressing on the nerves or keeps collapsing, surgery can often correct the problem.
How Spinal Fracture Surgery Is Done
- Anesthesia and monitoring: You’ll be fully asleep. Nerve monitoring protects the spinal cord and nerves.
- Placing screws: Using X-ray or navigation guidance, screws are placed into the vertebrae above and below the fracture, often through small incisions (percutaneous fixation).
- Realigning the spine: Rods are connected to the screws and used to restore the spine’s alignment and height.
- Decompression, if needed: Bone fragments or other tissue pressing on the spinal cord or nerves are removed.
- Reconstruction, if needed: For a badly crushed vertebra, the front of the spine may be rebuilt with a cage or bone graft through a corpectomy.
- Fusion, when needed: Bone graft is placed so the injured levels heal together. Some fractures heal without a fusion, and the screws can be removed later.
- Closing: The incisions are closed with dissolvable stitches and skin glue.
Watch how screws and rods are placed through small incisions:
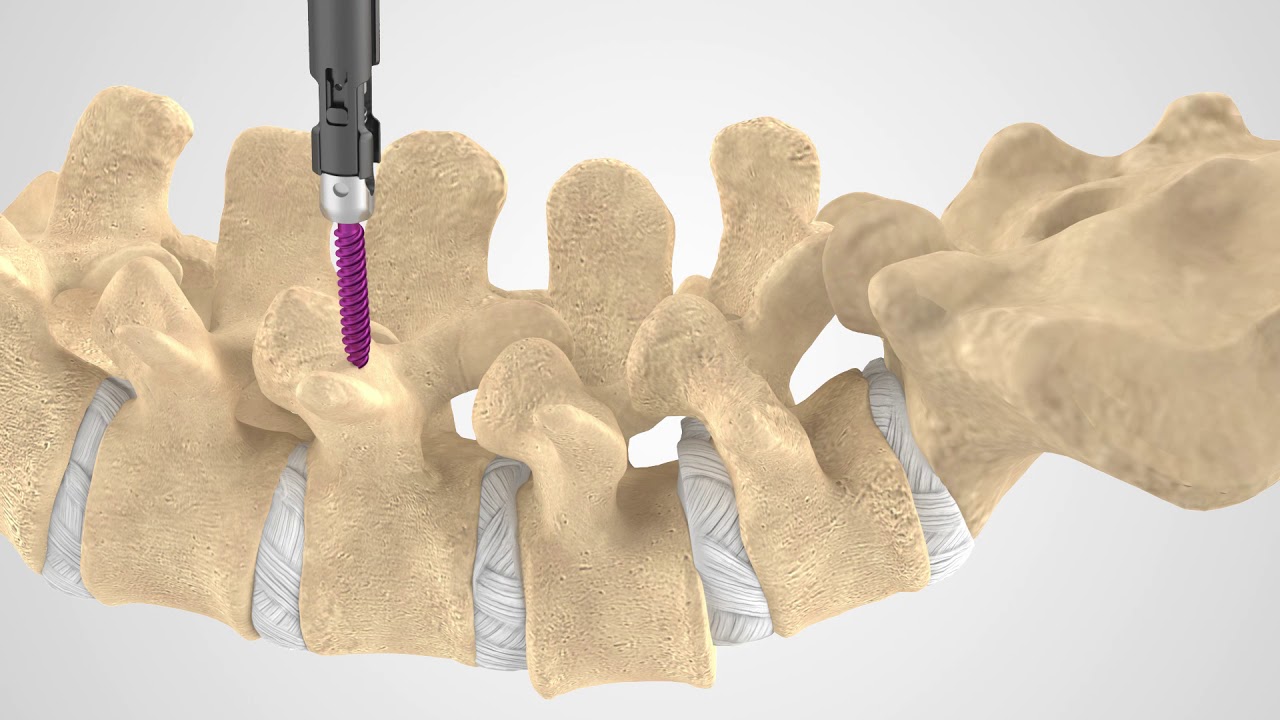
Video: MAS Fixation Patient Education Animation, courtesy of NuVasive (YouTube)
Benefits and Risks
Benefits
- A stable spine that protects the spinal cord and nerves
- Better pain control and an earlier return to walking
- Restored alignment and less chance of the spine collapsing or rounding forward
- A chance for nerve function to recover when pressure is relieved
- Often less time in a brace or in bed
Risks
- Infection or bleeding
- Nerve or spinal cord injury, which is uncommon
- Screw loosening or breakage, or the bones not healing, which can require another surgery
- Problems at the levels next to the repair over time
- Risks related to anesthesia, including blood clots and pneumonia
Nerve damage from the original injury may not fully recover, even with successful surgery. Your surgeon will talk with you and your family about what to expect.
What to Expect
In the hospital
Spinal fracture surgery is usually done in the hospital soon after an injury. Your care team will review your X-rays, CT and MRI, check your strength and sensation, and explain the plan to you and your family. If you take blood thinners, they will be paused or reversed when it’s safe. Smoking and nicotine slow bone healing, so stopping during recovery is strongly recommended.
Procedure day
Surgery usually takes two to four hours, depending on the fracture and how many levels are treated. Most patients stay in the hospital for two to five days, longer after a serious injury. You’ll be up and walking with physical therapy as soon as it’s safe, often the day after surgery.
Recovery timeline
- First two weeks: Walk several times a day and wear your brace if one is prescribed. Soreness is normal.
- Four to six weeks: Your follow-up visit, with X-rays to check healing and alignment.
- Six to twelve weeks: Restrictions are gradually lifted, and physical therapy helps rebuild strength.
- Three to twelve months: The fracture heals and, if you had a fusion, the bones fuse. Most people return to normal activities.
Every patient heals differently. Your recovery will depend on the type of fracture, any nerve injury and your overall health.
Caring for yourself at home
- Back brace: Wear your brace whenever you’re out of bed and moving around.
- Walking: Walk 30 to 60 minutes a day, broken into 10- to 15-minute sessions, and try not to sit for more than 30 minutes at a time.
- Restrictions for about six weeks: No bending at the waist, no twisting and no lifting more than 10 pounds. That includes vacuuming, laundry, golf, yard work and lifting young children or grandchildren. Let others help you at home.
- Your incisions: If your incisions are closed with skin glue, you may shower the day after surgery; if they have stitches or staples, wait three days. Don’t scrub, don’t use ointments or creams, and don’t soak in a bath, hot tub or pool for six weeks.
- Medications: Most patients use pain medication and a muscle relaxer for four to six weeks. Avoid anti-inflammatory medications such as ibuprofen, naproxen, meloxicam, celecoxib and diclofenac, which can interfere with fusion. Blood thinners are held for 5 to 7 days after surgery until your surgical team tells you to restart them. Take pain medication with food, avoid alcohol while taking it, and use a daily stool softener.
- Bone growth stimulator: If one is prescribed, the manufacturer will contact you after surgery.
- Driving: You may drive once you are no longer taking narcotic pain medication, and you may ride as a passenger before then.
- Follow-up: Your follow-up visit with Dr. Grunch or the surgeon who treated you in the hospital is about four to six weeks after surgery. Any outside stitches or staples are removed at 10 to 14 days.
Learn how a bone growth stimulator can support your fusion:

Video: Spinal Fusion Patients: Are You Using a Bone Growth Stimulator?, from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Call Dr. Grunch’s office at 470-293-9800, or the surgeon who treated you in the hospital, if you have a fever over 101°F, redness, warmth or significant drainage from the incision, calf pain or swelling, constipation that medication doesn’t relieve, new trouble controlling your bladder or bowels, or worsening pain down your leg. Call 911 for chest pain or shortness of breath.
Download your patient instructions
Print these sheets or save them to your phone so you have them before and after surgery:
You’ll find instructions for other procedures on our Patient Resources page.
Frequently Asked Questions
Does every spinal fracture need surgery?
No. Most stable fractures heal with a brace and time. Surgery is recommended when a fracture is unstable, pressing on the nerves or likely to collapse.
What is a burst fracture?
A burst fracture happens when a vertebra is crushed from above and below, usually in a fall or car accident, and breaks into several pieces. Fragments can push into the spinal canal and press on the spinal cord or nerves.
Will I need a fusion?
Not always. Some fractures are held with screws and rods just long enough to heal, and the hardware may be removed later. Others need a fusion for long-term stability. Your surgeon will explain which is right for you.
Will I have to wear a brace?
Some patients do for several weeks after surgery, especially when the bone is weak. Our team will tell you if you need one and for how long.
Can nerve damage improve after surgery?
Sometimes. Relieving pressure gives the nerves the best chance to recover, but recovery depends on how severe the original injury was.
Follow-Up Care After Hospital Treatment
For a new spine injury or sudden weakness, numbness, or trouble controlling your bladder or bowels, call 911 or go to the nearest emergency room.
Spinal fractures that need surgery are usually treated in the emergency room and hospital. After you go home, follow-up with Dr. Grunch or the surgeon who treated you in the hospital is an important part of recovery, including X-rays to check healing and guidance on returning to work, driving and normal activities. If Dr. Grunch cared for you in the hospital, or you’ve been referred for follow-up, call 470-293-9800 to schedule your visit or contact us online.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Burst fractures · Vertebral fractures · Compression fractures · Spinal cord injury · Kyphoplasty · Vertebral corpectomy
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.