
Minimally Invasive Lumbar Fusion From the Side
When a worn or unstable disc in the lower back is causing pain, a lateral lumbar interbody fusion (LLIF) can often correct the problem through a small incision on the side, restoring the disc space and stabilizing the spine without disturbing the back muscles.
What Is an LLIF?
A lateral lumbar interbody fusion, or LLIF, is a minimally invasive type of lumbar fusion done from the side of the body. You may also hear it called XLIF (extreme lateral interbody fusion) or DLIF (direct lateral interbody fusion), which are brand names for the same idea.
Through a small incision on your side, the surgeon passes between the fibers of the psoas muscle, which runs along the spine, to reach the disc. The disc is removed and replaced with a wide spacer filled with bone graft. Because the spacer rests on the strongest outer rim of the vertebrae, it supports the spine well and restores disc height, which opens up the nerve passages without having to work directly around the nerves.
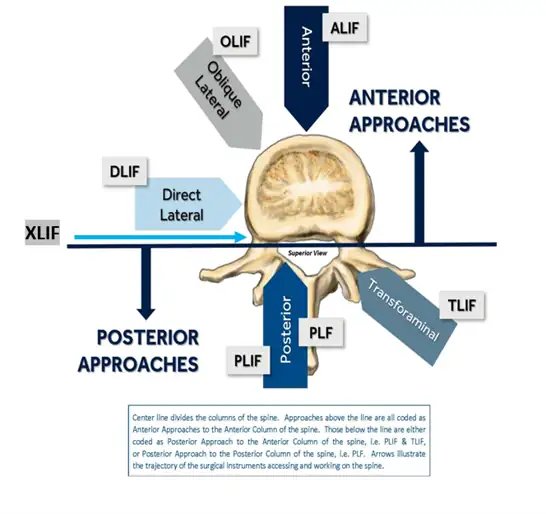
LLIF is well suited to the upper and middle levels of the lower back, from about L1-L2 to L4-L5. The pelvis blocks side access to L5-S1, so that level is usually treated with an ALIF or TLIF instead.
Who Needs an LLIF?
- Degenerative disc disease or a collapsed disc causing back and leg pain
- Spondylolisthesis or spinal instability
- Foraminal stenosis or spinal stenosis that can be relieved by restoring disc height
- Adult degenerative scoliosis, where lateral spacers help straighten and balance the spine
- Adjacent segment disease above a previous fusion, which can often be treated without reopening the old incision
Not every level or every patient is a fit for a lateral approach. Dr. Grunch reviews where your blood vessels, nerves and pelvis sit on your imaging to decide whether LLIF, ALIF or TLIF is the safest choice for you. She also performs OptiLIF (percutaneous lateral lumbar fusion) for selected patients.
Treatments to Try First
- Physical therapy: core strengthening and a structured exercise program
- Medications: anti-inflammatory medications, muscle relaxers or nerve pain medications
- Injections: epidural steroid injections, facet injections or radiofrequency ablation
- Activity changes and weight management to reduce stress on the spine
When these no longer keep you active, or nerves are being compressed by slipping or instability, surgery can often correct the problem.
How an LLIF Is Done
- Anesthesia and positioning: You’ll be fully asleep and lying on your side.
- Nerve monitoring: Real-time nerve monitoring is used to locate and protect the nerves that run through the psoas muscle.
- Reaching the spine: Through a small incision on your side, the surgeon gently separates the fibers of the psoas muscle, rather than cutting through it, to reach the disc.
- Removing the disc: The damaged disc is removed and the bone surfaces are prepared so they can fuse.
- Placing the spacer: A wide spacer filled with bone graft is placed across the disc space to restore height and alignment.
- Stabilizing: Screws and rods are usually placed through small incisions in the back, sometimes without needing to turn you over.
- Closing: The incisions are closed with dissolvable stitches and skin glue.
Watch an animation of how a lateral fusion is done:
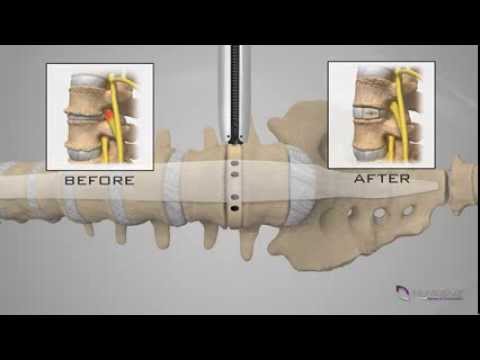
Video: XLIF Patient Animation, courtesy of NuVasive (YouTube)
Benefits and Risks
Benefits
- Small incisions and less disturbance of the back muscles
- Usually less blood loss and a shorter hospital stay than open fusion
- A wide spacer that restores disc height and indirectly relieves pressure on the nerves
- Helpful for correcting curves and for treating levels above an old fusion
Risks
- Temporary numbness, tingling or weakness in the front of the thigh or groin, or weakness lifting the hip, from working through the psoas muscle; this usually improves over weeks to months
- Infection or bleeding
- Injury to the bowel, kidney or blood vessels, which is rare
- The spacer settling into the bone (subsidence)
- The bones not fusing (nonunion), which is more common in people who smoke
- Extra wear at the levels above or below the fusion over time (adjacent segment disease)
- Risks related to anesthesia, including blood clots
Why Choose Dr. Betsy Grunch for Your LLIF
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country, where she received the Spine Young Investigator Award.
- Minimally invasive by design: Minimally invasive spine surgery is one of her signature areas, so you can get back on your feet sooner.
- Every approach: She performs TLIF, PLIF, ALIF and LLIF and chooses the approach that best fits your anatomy rather than using one technique for everyone.
- Fusion only when you need it: She also performs lumbar disc replacement and decompression without fusion, so a fusion is recommended only when it’s truly the best option for you.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- Second opinions and revisions: She regularly sees patients who had spine surgery elsewhere and want a second opinion or need a revision.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging, your exam and your goals, and to decide together whether an LLIF is right for you. Our team will coordinate any pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery so nothing is a surprise. Smoking and nicotine slow bone healing and can cause a fusion to fail, so stopping before surgery is strongly recommended. Our office can help.
Procedure day
Surgery usually takes two to four hours, depending on the number of levels and whether screws are placed in the back. Most patients stay in the hospital for one or two nights. You’ll be up and walking by the end of the first day after surgery, and physical therapy will help you get moving safely before you go home.
Recovery timeline
- First two weeks: Leg pain often improves quickly. Soreness in the side, back or thigh is normal. Walk several times a day and wear your brace when you’re up.
- Four to six weeks: Your follow-up visit, with X-rays to check healing. Many people with desk jobs return to work in three to six weeks.
- Six to twelve weeks: Restrictions are gradually lifted, and physical therapy may begin to strengthen your core and hips.
- Six to twelve months: The bones continue to fuse. Most patients are back to their normal activities.
Every patient heals differently. Your exact timeline will depend on your symptoms, the number of levels fused, your job and your overall health.
Caring for yourself at home
- Back brace: Wear your brace whenever you’re out of bed and moving around.
- Walking: Walk 30 to 60 minutes a day, broken into 10- to 15-minute sessions, and try not to sit for more than 30 minutes at a time.
- Restrictions for about six weeks: No bending at the waist, no twisting and no lifting more than 10 pounds. That includes vacuuming, laundry, golf, yard work and lifting young children or grandchildren. Let others help you at home.
- Your incisions: If your incisions are closed with skin glue, you may shower the day after surgery; if they have stitches or staples, wait three days. Don’t scrub, don’t use ointments or creams, and don’t soak in a bath, hot tub or pool for six weeks.
- Medications: Most patients use pain medication and a muscle relaxer for four to six weeks. Avoid anti-inflammatory medications such as ibuprofen, naproxen, meloxicam, celecoxib and diclofenac, which can interfere with fusion. Blood thinners are held for 5 to 7 days after surgery until Dr. Grunch’s team tells you to restart them. Take pain medication with food, avoid alcohol while taking it, and use a daily stool softener.
- Bone growth stimulator: If one is prescribed, the manufacturer will contact you after surgery.
- Driving: You may drive once you are no longer taking narcotic pain medication, and you may ride as a passenger before then.
- Follow-up: Your follow-up visit is about four to six weeks after surgery. Any outside stitches or staples are removed at 10 to 14 days.
Learn how a bone growth stimulator can support your fusion:

Video: Spinal Fusion Patients: Are You Using a Bone Growth Stimulator?, from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Call the office at 470-293-9800 if you have a fever over 101°F, redness, warmth or significant drainage from the incision, calf pain or swelling, constipation that medication doesn’t relieve, new trouble controlling your bladder or bowels, or worsening pain down your leg. Call 911 for chest pain or shortness of breath.
Download your patient instructions
Print these sheets or save them to your phone so you have them before and after surgery:
- About your surgery: Lateral Lumbar Interbody Fusion (PDF)
- Post-operative guidelines: Posterior or Lateral Lumbar Fusion (PDF)
You’ll find instructions for other procedures on our Patient Resources page.
Frequently Asked Questions
Is LLIF the same as XLIF or DLIF?
They are closely related. XLIF and DLIF are brand names for lateral fusions done through the psoas muscle. OLIF reaches the disc at an angle in front of the psoas. Dr. Grunch will explain which version she recommends for you.
Why does my thigh feel numb or weak?
The nerves that supply the front of the thigh run through the psoas muscle. Even with careful nerve monitoring, they can be irritated during surgery. This is usually temporary and improves over weeks to months.
Can LLIF be used at L5-S1?
Usually not. The pelvis is in the way at L5-S1, so that level is typically treated with an ALIF or TLIF.
Will I need screws in my back?
Most patients do. Screws and rods placed through small incisions in the back hold the spacer steady while the bone heals. In some cases the spacer is secured from the side alone.
How long does it take for the fusion to heal?
The spacer and any screws hold the spine steady right away, but the bone takes about six to twelve months to fully fuse. Not smoking, good nutrition and staying active all help.
Take the First Step Toward Relief
If back or leg pain from a worn or unstable spine is keeping you from living your life, you have options. Whether you need a treatment plan, a second opinion or a clear explanation of your imaging, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Lumbar fusion · ALIF · TLIF · OptiLIF · Minimally invasive fusion · Adjacent segment disease
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.