
Giving a Swollen Brain Room to Heal
Severe head injuries, strokes and brain bleeds are emergencies. If someone has a head injury or sudden weakness, numbness, trouble speaking, confusion or a severe headache, call 911 or go to the nearest emergency room.
When the brain swells after a severe injury or stroke, the skull leaves it nowhere to go. A decompressive craniectomy can be lifesaving by giving the swollen brain room to expand while it heals.
What Is a Decompressive Craniectomy?
A decompressive craniectomy is surgery to remove a large section of the skull so a swollen brain can expand without being crushed. Unlike a craniotomy, the bone is not put back at the end of surgery. The bone flap is usually stored frozen, or sometimes placed under the skin of the abdomen, and is replaced in a later surgery called a cranioplasty once the swelling has gone down.
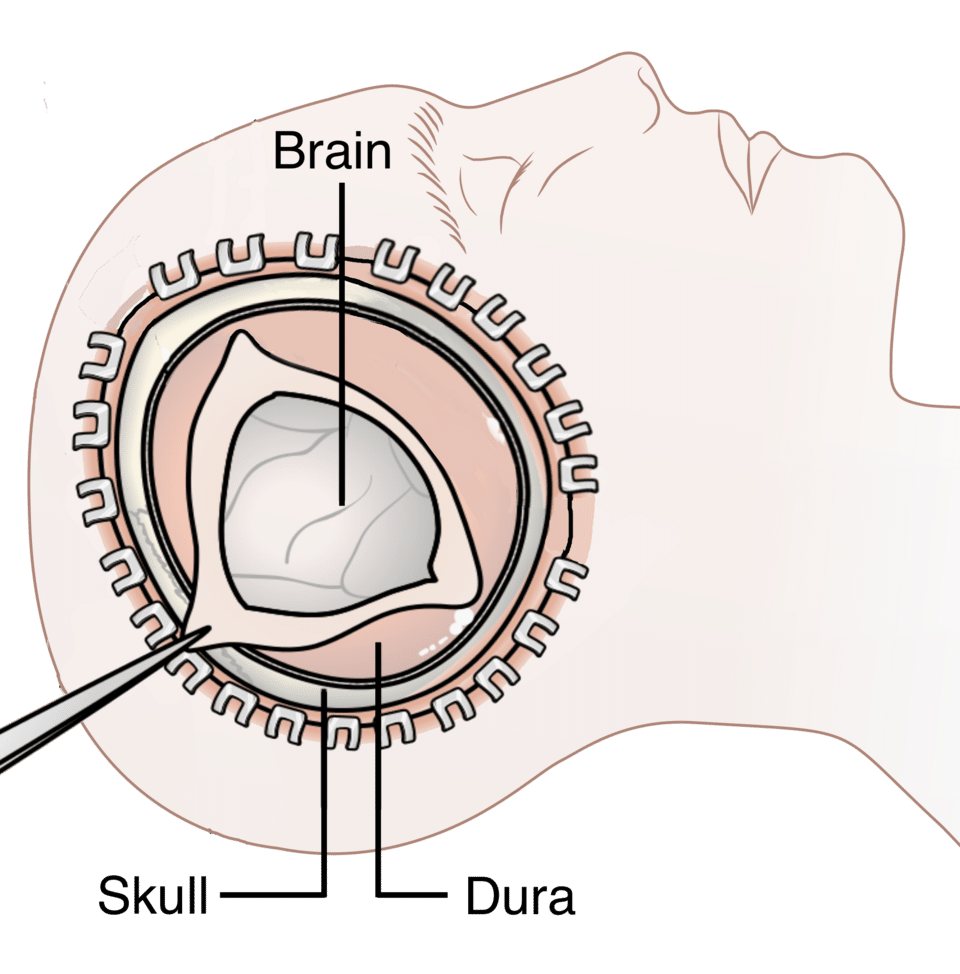
When the bone is removed from one side of the head it is called a hemicraniectomy. When it is removed from the front of the head, it is called a bifrontal craniectomy.
Who Needs a Decompressive Craniectomy?
- Severe traumatic brain injury with dangerous brain swelling
- A large stroke with swelling that is pushing the brain aside
- A large subdural hematoma or brain bleed with swelling
- High pressure inside the skull that isn’t controlled with medicines and other treatments
Treatment Without Surgery
- Intensive care: breathing support, sedation and careful control of blood pressure
- Medicines that reduce swelling: such as hypertonic saline or mannitol
- Pressure monitoring and drainage: a monitor or drain placed in the skull to measure and lower pressure
When the pressure keeps rising despite these treatments, a decompressive craniectomy can relieve it.
How a Decompressive Craniectomy Is Done
- Emergency anesthesia: The patient is fully asleep, often already on a breathing machine.
- Removing the bone: A large section of skull is removed over the swollen area.
- Treating the cause: Any blood clot is removed, and the dura is opened and loosely patched to give the brain more room.
- Closing: The scalp is closed over the opening. The bone flap is stored for later.
- Cranioplasty later: Usually 6 to 12 weeks later, once the swelling has gone down, the patient’s own bone or a custom implant is placed back in a separate surgery.
Watch Dr. Grunch explain a hemicraniectomy:
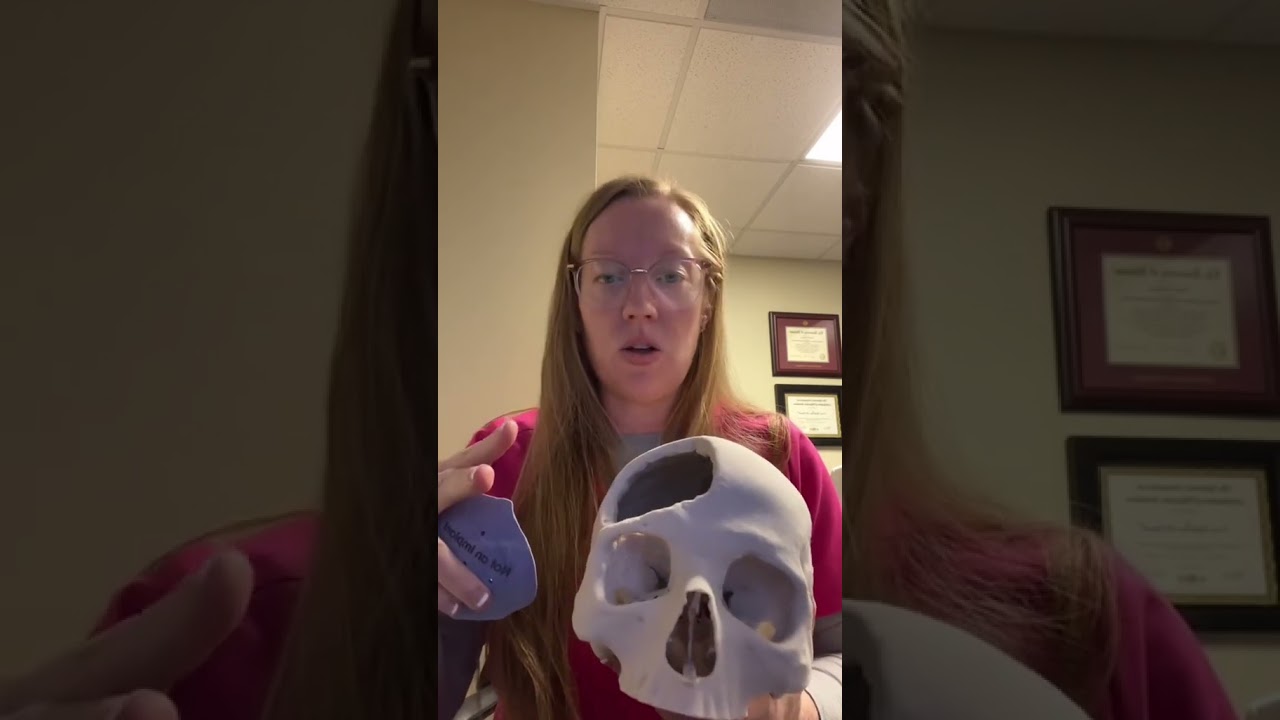
Video: Hemicraniectomy, a Lifesaving Procedure, explained by Dr. Grunch on her Ladyspinedoc channel (YouTube)
Learn how the skull is rebuilt with a cranioplasty:

Video: Performing a Cranioplasty, courtesy of the American Association of Neurological Surgeons (YouTube)
Cranioplasty: Putting the Bone Back
A decompressive craniectomy is almost always followed by a second surgery called a cranioplasty. It is typically performed 6 to 12 weeks after the craniectomy, once the brain swelling has gone down, to place the patient’s own bone back or, if the bone can’t be used, a custom implant. This restores protection for the brain and the shape of the head, and the protective helmet is no longer needed afterward.
Benefits and Risks
Benefits
- Lowers dangerous pressure inside the skull
- Can be lifesaving after a severe injury or large stroke
- Protects healthy brain from further damage while the swelling resolves
Risks
- Infection
- Bleeding
- A collection of fluid under the scalp or problems with spinal fluid flow (hydrocephalus)
- Seizures
- Survival with significant disability, depending on the original injury
- Risks of the later cranioplasty, including infection or problems with the bone flap
This surgery is often done when a life is in danger, and the outcome depends mostly on the severity of the original injury or stroke. Your surgeon will talk honestly with your family about goals and expectations.
What to Expect
In the hospital
A decompressive craniectomy is done as an emergency, and patients are cared for in the intensive care unit afterward, often for days to weeks. The care team will keep your family updated and involve them in decisions. Many patients go on to an inpatient rehabilitation program.
Recovery timeline
- Intensive care: Close monitoring of brain pressure, breathing and blood pressure.
- Rehabilitation: Physical, occupational and speech therapy, often for weeks to months.
- Cranioplasty: Usually 6 to 12 weeks after the first surgery, when the swelling is gone and the patient is healthy enough.
- Beyond: Recovery from a severe brain injury or stroke can continue for a year or more.
Caring for yourself at home
- Your incision: You can usually shower after two to three days. Let water run gently over the incision and pat it dry. Don’t scrub, soak in a bath or pool, or use hair dye or harsh hair products until it has fully healed. Staples or stitches are usually removed in 10 to 14 days.
- Activity: Walk every day and rest when you’re tired. Avoid heavy lifting, bending over and straining for about four to six weeks, and avoid contact sports until you are cleared.
- Protecting the opening: Until the skull is rebuilt, the brain is protected only by the scalp. Wear your protective helmet whenever you are out of bed, and take precautions to prevent falls.
- Medications: Take any seizure medication exactly as prescribed and don’t stop it on your own. Don’t take blood thinners, aspirin or anti-inflammatory medications such as ibuprofen until your surgical team tells you it’s safe. Take pain medication with food, avoid alcohol and use a stool softener so you don’t strain.
- Driving: Don’t drive until you are cleared. If you have had a seizure, Georgia law limits driving for a period of time.
- Recovery at home: Fatigue, headaches and trouble concentrating are common for several weeks. Have someone stay with you for the first few days.
Call Dr. Grunch’s office at 470-293-9800, or the surgeon who treated you in the hospital, if you have a fever over 101°F, redness, swelling or drainage from the incision, clear fluid leaking from the incision or nose, or calf pain or swelling. Call 911 for a seizure, a sudden severe headache, new confusion or drowsiness, new weakness or numbness, trouble speaking, chest pain or shortness of breath.
Frequently Asked Questions
Where does the bone go?
It’s usually stored frozen in a tissue bank at the hospital. Sometimes it is placed under the skin of the abdomen to keep it healthy until it can be replaced.
When is the bone put back?
Usually 6 to 12 weeks later, once the swelling is gone. If the bone can’t be used, a custom implant is made instead.
Why does a helmet need to be worn?
Without the bone, the brain is protected only by the scalp. A helmet protects it from injury until the cranioplasty.
Will the person recover?
Recovery depends mainly on the severity of the original injury or stroke. Some people recover well, while others have lasting disabilities. Your care team will keep you informed along the way.
Why does the scalp look sunken?
As the swelling goes down, the scalp may sink in over the opening, especially when sitting up. This is expected until the cranioplasty.
Follow-Up Care After Hospital Treatment
For a new head injury or sudden symptoms, call 911 or go to the nearest emergency room.
A decompressive craniectomy is performed as an emergency in the hospital. After you go home, follow-up with Dr. Grunch or the surgeon who treated you in the hospital is an important part of recovery, including repeat imaging, checking your incision and guidance on returning to work, driving and normal activities. If Dr. Grunch cared for you in the hospital, or you’ve been referred for follow-up, call 470-293-9800 to schedule your visit or contact us online.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Cranioplasty · Intracranial hemorrhage · Subdural hematoma · Diffuse axonal injury · Craniotomy · Subdural hematoma evacuation
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. If you or someone else has a head injury with confusion, worsening headache, repeated vomiting, a seizure, unequal pupils, weakness or trouble waking up, call 911 or go to the nearest emergency room.