
Removing Tumors In and Around the Spinal Cord
Hearing that you have a tumor in or around your spinal cord is frightening. Many spinal tumors are benign and slow-growing, and when a tumor is pressing on the spinal cord or nerves, spinal cord tumor resection can often correct the problem by removing the tumor and protecting your strength and sensation.
What Is Spinal Cord Tumor Resection?
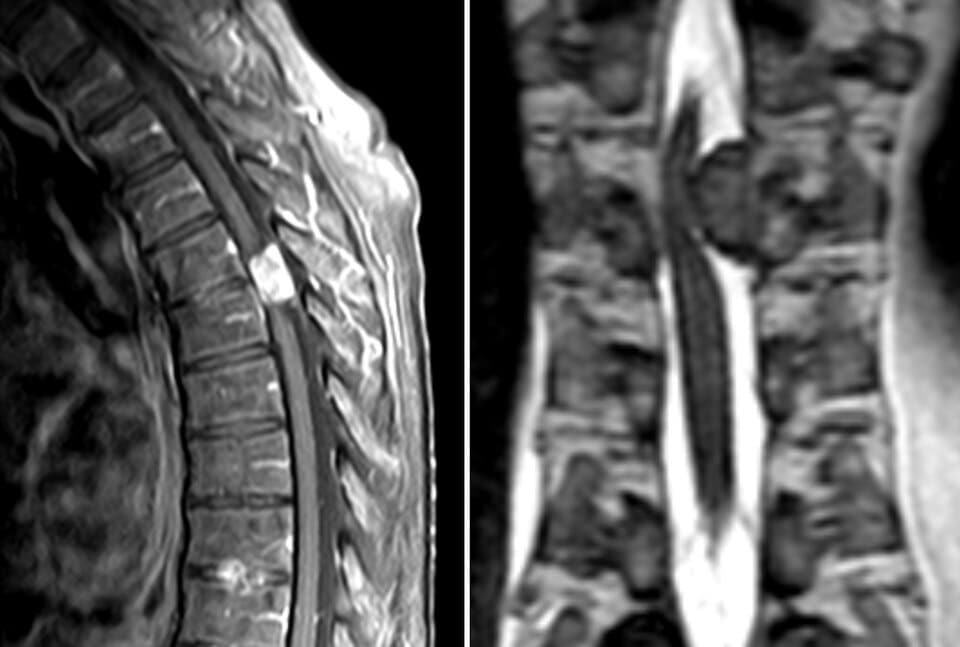
Spinal cord tumor resection is surgery to remove a tumor from inside the spinal canal. Surgeons describe spinal tumors by where they grow:
- Intradural extramedullary tumors: grow inside the covering of the spinal cord (the dura) but outside the cord itself. These are the most common intradural tumors and include spinal meningiomas and nerve sheath tumors such as schwannomas. Most are benign and can often be removed completely.
- Intramedullary tumors: grow inside the spinal cord itself, such as ependymomas and astrocytomas. These are less common and more delicate to remove.
- Extradural tumors: grow outside the dura, most often cancer that has spread to the spine. These are covered on our extradural tumors page.
Who Needs Spinal Cord Tumor Resection?
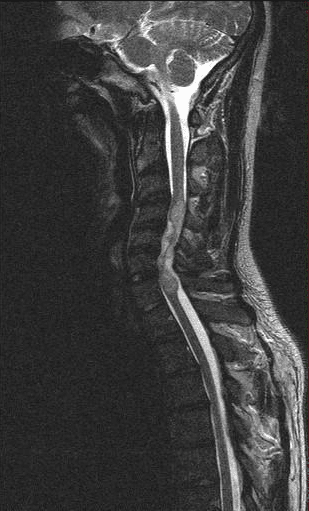
- A tumor pressing on the spinal cord or nerves, causing back or neck pain, numbness, weakness, balance problems or bladder changes
- A tumor that is growing on repeat MRI scans
- When tissue is needed to make an exact diagnosis
- Rapidly worsening symptoms, which can make surgery urgent
Treatments to Try First
- Observation: small tumors found by chance that aren’t causing symptoms are often watched with regular MRI scans
- Steroids: to reduce swelling around the spinal cord while a plan is made
- Radiation: including focused radiation (radiosurgery) for some tumors, or after surgery when a tumor can’t be fully removed
- Cancer treatment: chemotherapy and other therapies, coordinated with your oncology team, for some tumor types
When a tumor is growing or causing symptoms, surgery can often correct the problem.
How Spinal Cord Tumor Resection Is Done
- Planning: MRI with contrast shows the tumor’s size and exact location.
- Anesthesia and monitoring: You’ll be fully asleep. Nerve monitoring is used throughout surgery to check the signals traveling through your spinal cord.
- Opening: An incision is made in the middle of the back or neck, and a laminectomy removes the bony roof of the spinal canal over the tumor.
- Removing the tumor: Using the operating microscope, the surgeon opens the dura and carefully separates the tumor from the spinal cord and nerves.
- Closing: The dura is closed watertight, and the muscles and skin are closed. A fusion is added only when the spine needs extra support.
Watch Dr. Grunch explain a spinal cord meningioma case:

Video: Case Study 37, Cervical Myelopathy and Spinal Cord Meningioma, presented by Dr. Grunch on her Ladyspinedoc channel (YouTube)
Benefits and Risks
Benefits
- Relieves pressure on the spinal cord and nerves
- Can stop or reverse numbness, weakness and balance problems
- Provides an exact diagnosis to guide any further treatment
- Many benign tumors can be removed completely
Risks
- New or worsened numbness, weakness or bladder problems, which are often temporary
- A spinal fluid leak from the dura repair
- Infection or bleeding
- The tumor coming back, especially if part of it couldn’t be safely removed
- Instability of the spine over time, which may need a fusion
- Risks related to anesthesia
Why Choose Dr. Betsy Grunch for Your Spinal Cord Tumor Surgery
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country.
- Honest guidance: Dr. Grunch reviews your MRI and tells you whether watching, surgery or another treatment makes the most sense, and coordinates with oncology and radiation teams when needed.
- Nerve monitoring and microsurgery: Spinal cord surgery is done under the operating microscope with continuous nerve monitoring to protect strength, sensation and bladder function.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining brain and spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your CT or MRI, your symptoms and your goals, and to decide together whether surgery is right for you. Our team will coordinate pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery. You’ll have an MRI with contrast, and sometimes other scans, to plan the safest approach.
Procedure day
Surgery usually takes three to six hours, depending on the tumor. Most patients stay in the hospital for three to five days. Some benefit from a short stay in an inpatient rehabilitation center before going home.
Recovery timeline
- First days: Getting up to walk with physical therapy. Some numbness or weakness right after surgery is common and often improves.
- Two weeks: Stitches or staples are removed, and the pathology results are reviewed with you.
- Four to six weeks: A follow-up visit. Many people return to desk work around this time.
- Three months and beyond: Strength and sensation can keep improving for many months. Follow-up MRIs check that the tumor hasn’t returned.
Caring for yourself at home
- Your incision: If it is closed with skin glue, you may shower the day after surgery; if it has stitches or staples, wait three days. Pat it dry and don’t use ointments or creams. Don’t soak in a bath, hot tub or pool for six weeks. Stitches or staples are usually removed in 10 to 14 days.
- Activity: Walk several times a day. Avoid bending, twisting, straining and lifting more than 10 pounds for about four to six weeks.
- Lying flat: Because the covering of the spinal cord is opened and sewn closed, you may be asked to lie flat for the first day or two to protect the repair.
- Medications: Take pain medication with food, avoid alcohol while taking it and use a daily stool softener so you don’t strain. Don’t restart blood thinners until Dr. Grunch’s team tells you it’s safe.
- Driving: You may drive once you are off narcotic pain medication and can turn and react comfortably.
Call the office at 470-293-9800 if you have a fever over 101°F, redness, swelling or drainage from the incision, clear fluid leaking from the incision, a headache that is worse when you sit or stand, or calf pain or swelling. Call 911 for new weakness or numbness, loss of bladder or bowel control, chest pain or shortness of breath.
Download your patient instructions
Your instructions depend on the type of surgery you have. Our team will give you written instructions before you go home, and you’ll find other patient sheets on our Patient Resources page.
Frequently Asked Questions
Is my spinal tumor cancer?
Most tumors that grow inside the covering of the spinal cord, such as meningiomas and schwannomas, are benign. The pathology report after surgery confirms the exact type.
Can the whole tumor be removed?
Many benign intradural tumors can be removed completely. Tumors inside the spinal cord, or tumors tightly attached to it, are sometimes partly removed to protect function, and may be followed with MRI or treated with radiation.
Will I need a fusion?
Usually not. A fusion is added only if removing bone to reach the tumor would leave the spine unstable.
Will my numbness and weakness get better?
Often, yes, especially when surgery is done before the symptoms become severe. Improvement can continue for many months.
Can the tumor come back?
It can, which is why follow-up MRI scans are part of your care.
Take the Next Step
If you’ve been told you have a tumor in or around your spinal cord, you don’t have to navigate it alone. Whether you need a diagnosis, a treatment plan or a second opinion, Dr. Grunch and the Southern Neurosurgery team are here to help you understand your options.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Spinal cord tumors · Intradural tumors · Spinal meningiomas · Schwannomas · Extradural tumors · Spinal cord compression
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. If you have sudden weakness, numbness, loss of bladder or bowel control, or a sudden severe headache, call 911 or go to the nearest emergency room.