
Answers and Options When a Fusion Hasn’t Worked
If your pain came back, never went away, or new problems appeared after a spinal fusion, you’re not out of options. A revision fusion can often correct the problem, and a fresh look from a surgeon who regularly treats these cases can make all the difference.
What Is a Revision Fusion?
A revision fusion is a surgery to correct or improve a previous spinal fusion. It may involve fusing a level that never healed, replacing loose or broken screws and rods, extending the fusion to a neighboring level that has worn out, decompressing nerves, or correcting alignment that wasn’t restored the first time.
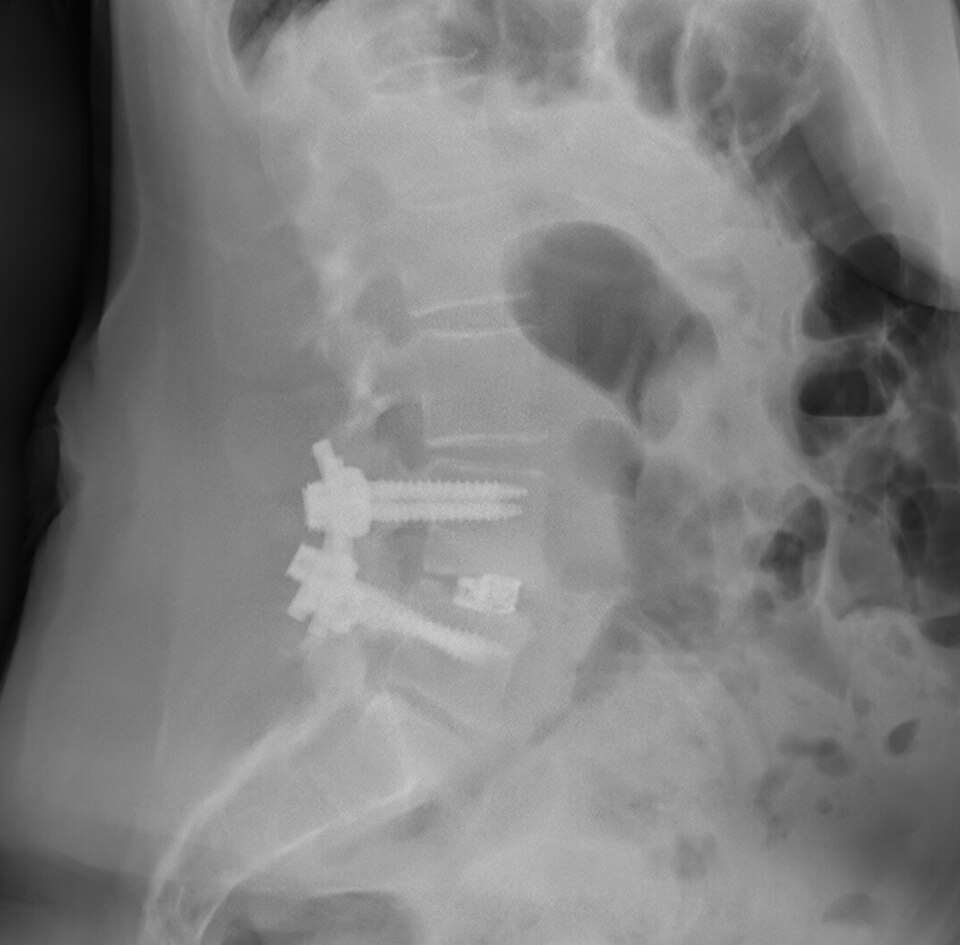
Revision surgery is more complex than a first surgery because of scar tissue, existing implants and changes in the anatomy. Careful planning, the right imaging and experience with revision cases are key to a good result.
Why Might a Revision Fusion Be Needed?
- Nonunion (pseudarthrosis): the bones never fused solidly, often causing ongoing pain and loose hardware
- Hardware problems: screws or rods that have loosened, broken or are irritating a nerve
- Adjacent segment disease: the level above or below the fusion has worn out, causing stenosis or instability
- Remaining nerve compression: narrowing that wasn’t fully treated or has developed since
- Flatback syndrome or sagittal imbalance: loss of the spine’s normal curve, making it hard to stand upright
- Infection involving the implants
Many patients with these problems have been told they have failed back surgery syndrome. Finding the specific cause is the first step to fixing it.
How We Evaluate You
Dr. Grunch starts by finding out exactly why you’re still hurting. Your evaluation may include:
- A detailed history of your symptoms before and after your surgery, and your operative reports
- Standing and bending X-rays to check for motion, alignment and hardware problems
- A CT scan to see whether the bones have fused and whether the screws are loose
- An MRI, often with contrast, to look for nerve compression and adjacent level problems
- Lab tests if an infection is a concern, and a bone density scan if bone quality is a concern
Treatments to Try First
Not every problem after a fusion needs another operation. Physical therapy, medications, injections, and in some cases a spinal cord stimulator, can help. When there’s a clear structural problem, such as nonunion, loose hardware or nerve compression, surgery can often correct the problem.
How a Revision Fusion Is Done
Every revision is planned around your specific problem. Depending on what’s needed, Dr. Grunch may:
- Remove and replace hardware: loose or broken screws are replaced, often with larger screws or reinforced fixation.
- Decompress nerves: scar tissue, bone or disc pressing on the nerves is carefully removed.
- Add an interbody fusion: a spacer with bone graft may be placed from the back, side or front to improve the chance of fusion.
- Extend the fusion: a worn-out neighboring level is decompressed and added to the fusion.
- Correct alignment: when needed, the spine’s curve is restored to help you stand upright.
Approaching from the front or side of the spine, through untouched tissue, can sometimes avoid the scar tissue from your first surgery.
Benefits and Risks
Benefits
- A solid fusion and stable spine
- Relief of nerve pain from compression
- Improved alignment and posture
- Removal of painful or failing hardware
Risks
Revision surgery carries higher risks than a first surgery, and Dr. Grunch will discuss them with you in detail:
- Infection or wound healing problems
- A spinal fluid leak, which is more common when working through scar tissue
- Nerve injury
- Bleeding or blood clots
- The bones still not fusing, which is more common in people who smoke
- Pain that doesn’t fully resolve
- Risks related to anesthesia
Why Choose Dr. Betsy Grunch for Your Revision Fusion
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country, where she received the Spine Young Investigator Award.
- Minimally invasive by design: Minimally invasive spine surgery, including transforaminal approaches through Kambin’s triangle, is one of her signature areas, so you can get back on your feet sooner.
- Fusion only when you need it: She also performs lumbar and cervical disc replacement and decompression without fusion, so a fusion is recommended only when it’s truly the best option for you.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- Revision experience: Patients who had surgery elsewhere and are still in pain make up a regular part of her practice. She takes the time to find the true cause before recommending another operation.
- Second opinions and revisions: She regularly sees patients who had spine surgery elsewhere and want a second opinion or need a revision.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging, your exam and your goals, and to decide together whether a revision fusion is right for you. Our team will coordinate any pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery so nothing is a surprise. Smoking and nicotine slow bone healing and can cause a fusion to fail, so stopping before surgery is strongly recommended. Our office can help.
Procedure day
Revision surgery usually takes three to five hours or more, depending on what needs to be done. Most patients stay in the hospital for two to four nights.
Recovery timeline
- First two weeks: Walk several times a day and wear your brace when you’re up.
- Four to six weeks: Your follow-up visit, with X-rays to check healing.
- Six to twelve weeks: Restrictions are gradually lifted, and physical therapy may begin.
- Six to twelve months: The bones continue to fuse. Recovery from revision surgery often takes longer than from a first surgery.
Every patient heals differently. Your exact timeline will depend on your symptoms, the number of levels fused, your job and your overall health.
Caring for yourself at home
- Back brace: Wear your brace whenever you’re out of bed and moving around.
- Walking: Walk 30 to 60 minutes a day, broken into 10- to 15-minute sessions, and try not to sit for more than 30 minutes at a time.
- Restrictions for about six weeks: No bending at the waist, no twisting and no lifting more than 10 pounds. That includes vacuuming, laundry, golf, yard work and lifting young children or grandchildren. Let others help you at home.
- Your incision: If your incision is closed with skin glue, you may shower the day after surgery; if it has stitches or staples, wait three days. Don’t scrub, don’t use ointments or creams, and don’t soak in a bath, hot tub or pool for six weeks.
- Medications: Avoid anti-inflammatory medications such as ibuprofen, naproxen, meloxicam, celecoxib and diclofenac, which can interfere with fusion. Blood thinners are held for 5 to 7 days after surgery until Dr. Grunch’s team tells you to restart them. Take pain medication with food, avoid alcohol while taking it, and use a daily stool softener.
- Bone growth stimulator: If one is prescribed, the manufacturer will contact you after surgery.
- Driving: You may drive once you are no longer taking narcotic pain medication, and you may ride as a passenger before then.
- Follow-up: Your follow-up visit is about four to six weeks after surgery. Any outside stitches or staples are removed at 10 to 14 days.
Learn how a bone growth stimulator can support your fusion:

Video: Spinal Fusion Patients: Are You Using a Bone Growth Stimulator?, from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Call the office at 470-293-9800 if you have a fever over 101°F, redness, warmth or significant drainage from the incision, calf pain or swelling, constipation that medication doesn’t relieve, new trouble controlling your bladder or bowels, or worsening pain down your leg. Call 911 for chest pain or shortness of breath.
Download your patient instructions
For a lumbar revision fusion, print this sheet or save it to your phone so you have it after surgery:
You’ll find instructions for other procedures on our Patient Resources page.
Frequently Asked Questions
How do I know if my fusion failed?
Ongoing or returning pain, especially pain that worsens with movement, can be a sign. A CT scan is the best way to see whether the bones have fused and whether the screws are loose.
Is revision surgery as successful as a first surgery?
Results depend on the cause. When there’s a clear structural problem, such as nonunion, loose hardware or nerve compression, revision surgery can be very successful. Finding the right cause is the most important step.
I had surgery with another surgeon. Can I still see Dr. Grunch?
Yes. Dr. Grunch regularly sees patients for second opinions after surgery elsewhere. Bring your imaging and, if possible, your operative reports to your visit.
Why does smoking matter so much?
Nicotine slows bone healing and is one of the most common reasons a fusion doesn’t heal. Quitting before a revision greatly improves your chances.
Will I need a bone growth stimulator?
Some patients are prescribed one after revision surgery to help the fusion heal. Dr. Grunch will let you know if you need one.
Take the First Step Toward Relief
If you’re still hurting after a spinal fusion, you deserve answers. Whether you need a treatment plan, a second opinion or a clear explanation of your imaging, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Failed back surgery syndrome · Adjacent segment disease · Flatback syndrome · Lumbar fusion · Lumbar microdiscectomy and revision disc surgery
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.