
Relieving Pressure on the Spinal Cord in Your Neck
When the spinal cord in your neck is being squeezed, protecting it is the priority. A cervical laminectomy can often correct the problem by opening the spinal canal and giving the cord room again.
What Is a Cervical Laminectomy?
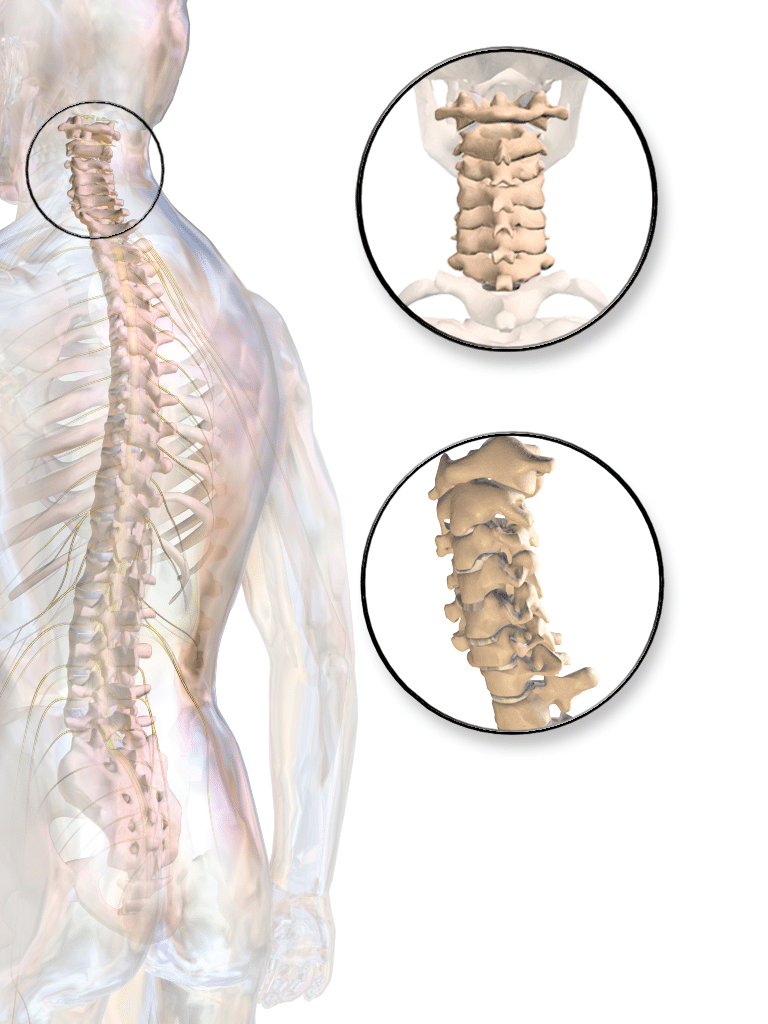
A cervical laminectomy is a surgery on the back of the neck that removes the lamina, the bony roof of the spinal canal, at one or more levels. It relieves pressure on the spinal cord and nerve roots caused by cervical spinal stenosis.
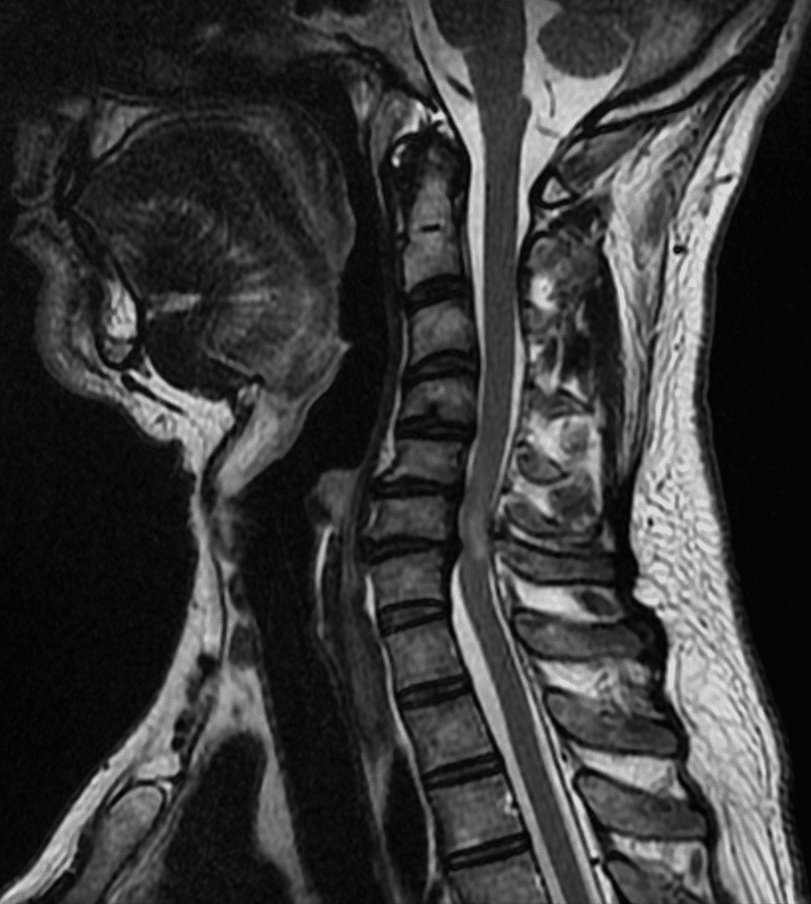
In the neck, stenosis is usually caused by arthritis (cervical spondylosis), bone spurs, thickened ligaments, bulging discs or OPLL, a condition where a ligament inside the canal turns to bone. When the spinal cord itself is compressed, it can cause cervical myelopathy, which tends to get worse slowly over time.
Because removing the lamina at several levels can change the way the neck is supported, a cervical laminectomy is often combined with a posterior cervical fusion. In some patients, a laminoplasty is a motion-preserving alternative. Dr. Grunch will explain which option fits your neck.
Who Needs a Cervical Laminectomy?
- Signs of spinal cord compression: clumsy hands, trouble with buttons or handwriting, dropping things, or feeling unsteady when you walk
- Numbness, tingling or weakness in the arms or legs
- Stenosis at several levels, especially when the pressure comes from the back of the canal
- An MRI showing compression of the spinal cord or nerves that matches your symptoms
Cervical myelopathy is different from many other spine problems: once the spinal cord is damaged, it may not fully recover. For that reason, surgery is often recommended before symptoms become severe.
Call 911 or go to the nearest emergency room if you have sudden weakness in your arms or legs, sudden trouble walking, or new trouble controlling your bladder or bowels.
Treatments to Try First
For neck pain or a pinched nerve without spinal cord compression, physical therapy, medications and injections are often tried first. When the spinal cord is compressed and causing symptoms, these treatments can’t relieve the pressure, and surgery can often correct the problem and help prevent further damage.
How a Cervical Laminectomy Is Done
- Anesthesia and monitoring: You’ll be fully asleep. Nerve monitoring is used during surgery to protect your spinal cord.
- Positioning: Your head is held securely in a padded frame, and you’re positioned face down.
- Incision: An incision is made in the middle of the back of the neck over the levels to be treated.
- Decompression: The lamina and thickened ligament are carefully removed to open the canal, and the openings for the nerve roots are widened if needed.
- Stabilizing, if needed: When a fusion is part of the plan, screws and rods are placed and bone graft is added so the levels heal together.
- Closing: The muscles and skin are closed in layers.
This animation from Spine-health shows how the procedure is performed:
Video: Cervical Laminectomy Video, courtesy of Spine-health.com
Benefits and Risks
Benefits
- Stops ongoing pressure on the spinal cord and helps prevent further damage
- Improves balance, hand function, numbness or arm pain for many patients
- Can treat several levels at once
Risks
- Infection or bleeding
- Spinal fluid leak
- Spinal cord or nerve injury, which is rare
- Temporary weakness lifting the arm at the shoulder (C5 palsy), which usually improves
- Neck pain or stiffness, or a change in the neck’s alignment if no fusion is done
- Risks related to anesthesia
Why Choose Dr. Betsy Grunch for Your Cervical Laminectomy
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country, where she received the Spine Young Investigator Award.
- Minimally invasive by design: Minimally invasive spine surgery is one of her signature areas. She works through the smallest opening that will safely do the job, so you can get back on your feet sooner.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- Every option for your neck: She performs cervical laminectomy, laminoplasty, posterior fusion, ACDF and cervical disc replacement, so your recommendation is based on what’s best for you.
- Second opinions and revisions: She regularly sees patients who had spine surgery elsewhere and want a second opinion or need a revision.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging, your exam and your goals, and to decide together whether a cervical laminectomy is right for you. Our team will coordinate any pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery so nothing is a surprise. If you smoke or use nicotine, stopping before surgery lowers the risk of complications.
Procedure day
The surgery usually takes two to four hours, depending on the number of levels and whether a fusion is included. Most patients stay in the hospital for one to two nights.
Recovery timeline
- First two weeks: Walk every day. Neck soreness is common. Avoid lifting, and keep your head in comfortable, neutral positions. Your first follow-up visit is about two weeks after surgery.
- Two to six weeks: Gradually increase your activity. Many patients return to desk work in four to six weeks.
- Six to twelve weeks: Dr. Grunch may start physical therapy for neck strength and balance.
- Three months and beyond: If a fusion was done, the bones keep healing. Balance and hand function may keep improving for months, depending on how long the cord was compressed.
Every patient heals differently. Your exact timeline will depend on your symptoms, your job and your overall health.
Frequently Asked Questions
Will I need a fusion too?
Often, yes. When several laminae are removed, a fusion helps keep the neck from gradually bending forward. Some patients are good candidates for a laminoplasty instead, which keeps more motion.
Will my hand clumsiness and balance get better?
The main goal is to stop the condition from getting worse. Many patients also improve, especially when surgery is done before symptoms are severe.
Will I wear a neck collar?
Sometimes a soft collar is used for comfort for a short time. Dr. Grunch will let you know if you need one.
Can I turn my head after surgery?
Yes, though motion may be somewhat reduced at fused levels. Most people adapt well for daily activities and driving.
When can I drive?
You may drive once you’re off narcotic pain medication and can turn your head comfortably to check your blind spots, usually two to four weeks after surgery.
Take the First Step Toward Relief
Neck stenosis and myelopathy can quietly steal your balance and hand skills. Whether you need a treatment plan, a second opinion or a clear explanation of your imaging, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Cervical myelopathy · Spinal stenosis · OPLL · Laminoplasty · Posterior cervical fusion
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.