
Discogenic Back Pain: When the Disc Itself Is the Source
Deep, aching back pain that’s worst when you sit, bend or lift, with no pain shooting down your leg, often comes from a damaged disc. Identifying it correctly opens the door to treatments that work, including disc replacement.
What Is Discogenic Back Pain?
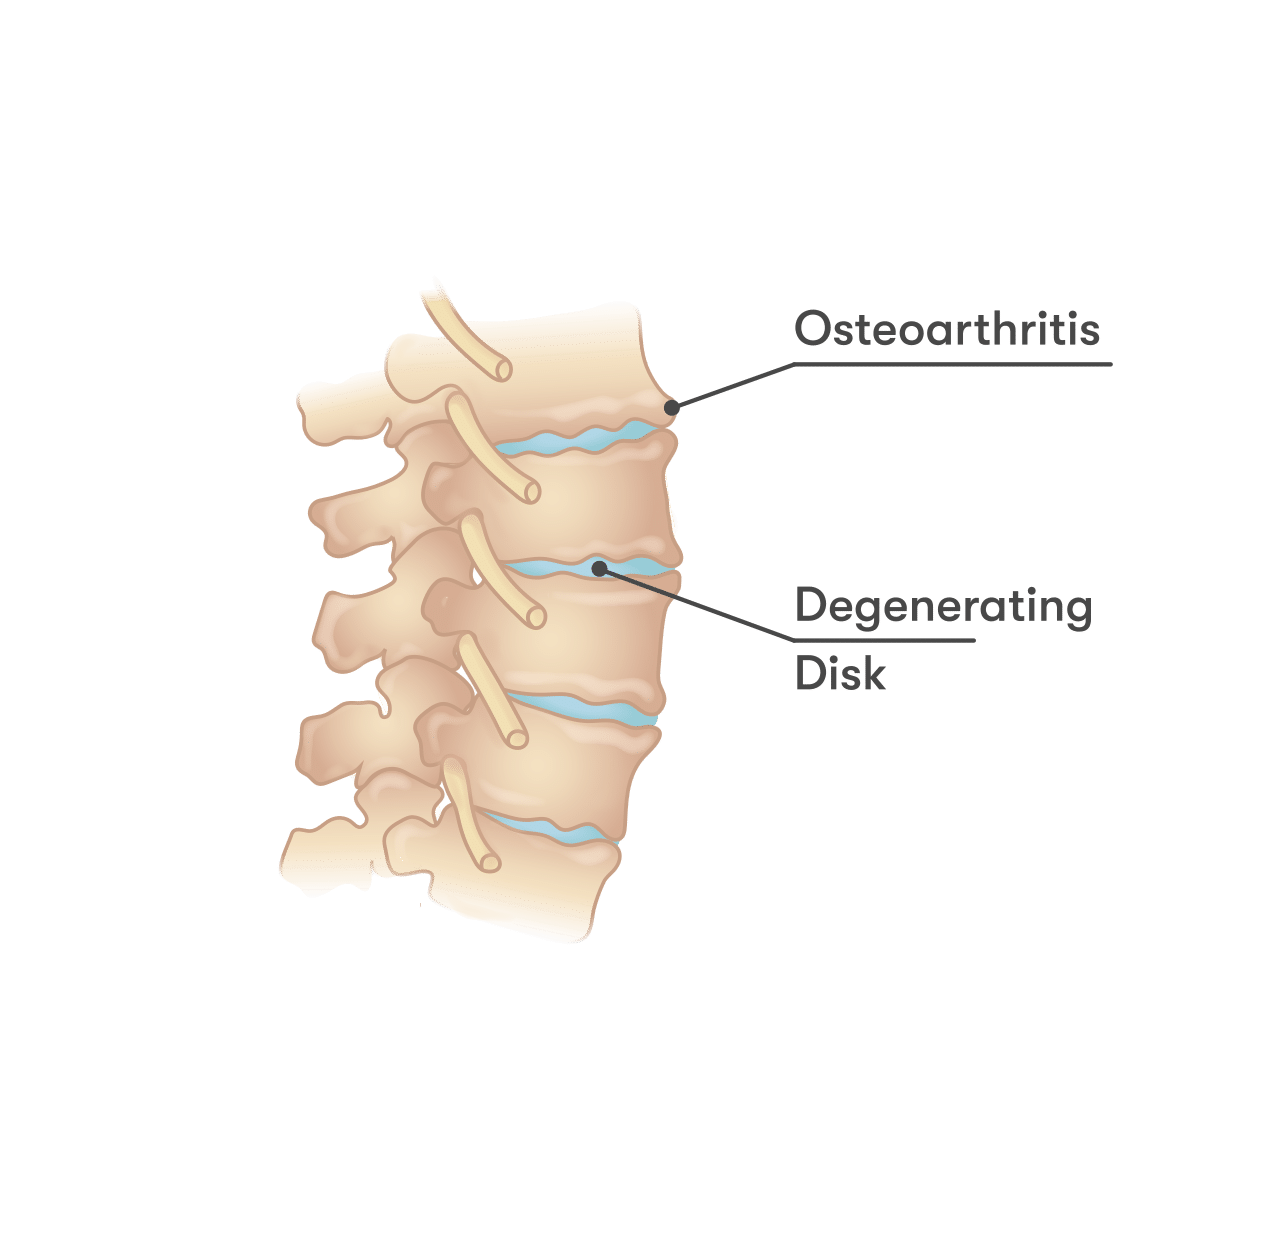
Discogenic pain is pain that comes from inside a spinal disc rather than from a pinched nerve. Each disc has a tough outer ring with nerve endings in its outer layers. When the disc wears down or develops tears in that ring, those nerve endings can become a source of ongoing pain.
Discogenic pain is closely related to degenerative disc disease. Not every worn disc hurts, but when a specific disc is the pain generator, treatment can be targeted at that disc.
Most people improve with exercise-based therapy and other conservative care. For carefully selected patients with persistent pain from one or two discs, artificial disc replacement or fusion can often correct the problem.
What’s Happening in the Disc
- Annular tears: small cracks in the outer ring of the disc that can become painful and inflamed
- Internal disc disruption: breakdown inside the disc that changes how it carries load
- Loss of water and height: the disc becomes a less effective cushion and shifts stress onto surrounding joints
- Inflammation in the endplates: the bone surfaces above and below the disc can also become painful
Symptoms
Common symptoms
- Deep, aching pain in the center of the low back (or neck)
- Pain that’s worse with sitting, bending forward, lifting, coughing or sneezing
- Relief when lying down or changing positions
- Pain that may spread into the buttocks or upper thighs without true sciatica
Symptoms patients often ignore
- Needing to stand up during long drives or meetings
- Pain getting up after sitting that eases after a few steps
- Flares after yard work or lifting that take days to settle
Pain, numbness or weakness that travels below the knee suggests a pinched nerve, which needs its own evaluation.
Risk Factors
- Age and genetics
- Smoking
- Repetitive bending, lifting or vibration
- Previous back injury
- Excess body weight
How We Diagnose Discogenic Pain
- History and exam: the pattern of pain and a neurological check to look for nerve involvement
- MRI: shows dark, dehydrated discs, tears and endplate changes
- Nociscan: a noninvasive analysis of a special MRI scan (MR spectroscopy) that measures chemical markers of pain inside each disc, helping identify which discs are likely painful and which are not, without needles
- Discography: contrast dye is injected into one or more discs under X-ray guidance to see whether it reproduces your usual pain, often followed by a CT scan that shows tears inside the disc. It can help confirm which disc is the pain source before surgery.
- X-rays with bending views: check disc height, alignment and stability
- Ruling out other pain sources: facet joints, SI joints and hips can cause similar pain and may be tested with diagnostic injections
Treatment Options
Non-surgical treatment comes first
- Physical therapy: core strengthening and movement-based programs that reduce disc pain
- Activity changes: breaking up long periods of sitting and using good lifting mechanics
- Medications: anti-inflammatories during flares
- Weight management and quitting smoking
- Injections: for pain relief and to help confirm the pain source
When surgery makes sense
Surgery is considered for patients with significant pain that persists despite several months of good conservative care, when imaging and exam clearly point to one or two discs. In these cases, surgery can often correct the problem:
- Lumbar artificial disc replacement: one of Dr. Grunch’s specialties. The painful disc is removed and replaced with a motion-preserving implant. Read Dr. Grunch’s guide to lumbar disc replacement.
- Minimally invasive fusion: when disc replacement isn’t the right fit, such as with significant facet arthritis or instability
- Cervical disc replacement: for selected patients with disc-related neck pain and nerve symptoms
Why Choose Dr. Betsy Grunch for Discogenic Back Pain
- Duke-trained: neurosurgical residency and spine research fellowship at Duke University School of Medicine, where she received the Spine Young Investigator Award
- Experience you can count on: in practice since 2013, performing 400 to 600 surgeries a year and more than 5,000 procedures over her career
- Disc replacement expertise: she performs both lumbar and cervical artificial disc replacement, so fusion isn’t your only surgical option
- The right treatment for you: board-certified (FAANS, FACS, FCNS), she starts with the least invasive option that will work, and recommends surgery when it can correct the problem
- Clear answers: known online as Ladyspinedoc, she makes sure you understand your imaging and every option in front of you
What to Expect If You Need Surgery
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging and determine whether you’re a candidate for disc replacement or fusion. Our team coordinates pre-operative testing and reviews your medications.
Procedure day
Lumbar disc replacement is performed through a small incision in the lower abdomen and usually involves one to two nights in the hospital.
Recovery timeline
- Day 1: up and walking
- Weeks 1-2: walking several times a day
- Weeks 2-6: many desk workers return to work; avoid heavy lifting
- Months 2-3: physical therapy and return to most activities
Frequently Asked Questions
How is discogenic pain different from sciatica?
Discogenic pain comes from the disc itself and is felt mainly in the back. Sciatica comes from a pinched nerve and runs down the leg, often below the knee.
Why does sitting hurt more than walking?
Sitting increases pressure inside the lower discs more than standing or walking, so a painful disc often hurts most when you sit.
Am I a candidate for disc replacement?
The best candidates have pain from one or two discs, without significant facet arthritis, instability or osteoporosis. Dr. Grunch will review your imaging and tell you honestly whether disc replacement fits your spine.
Will my disc heal on its own?
The disc doesn’t regenerate, but pain often improves over time as inflammation settles and supporting muscles get stronger.
Is a fusion or disc replacement better?
Both can be effective. Disc replacement preserves motion; fusion is preferred when the spine is unstable or arthritic. The right choice depends on your anatomy.
Take the First Step Toward Relief
Whether you need a diagnosis, a treatment plan or a second opinion, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
This page is for educational purposes only and is not a substitute for medical advice. If you have sudden weakness, numbness in the groin, or bladder or bowel changes, call 911 or go to the nearest emergency room.